All content on this site is intended for healthcare professionals only. By acknowledging this message and accessing the information on this website you are confirming that you are a healthcare professional. If you are a patient or carer, please visit Know AML.
The AML Hub website uses a third-party service provided by Google that dynamically translates web content. Translations are machine generated, so may not be an exact or complete translation, and the AML Hub cannot guarantee the accuracy of translated content. The AML Hub and its employees will not be liable for any direct, indirect, or consequential damages (even if foreseeable) resulting from use of the Google Translate feature. For further support with Google Translate, visit Google Translate Help.


The AML Hub is an independent medical education platform, sponsored by Daiichi Sankyo, Kura Oncology, Syndax, Abbvie, Thermo Fisher and Johnson & Johnson. Funders are allowed no direct influence on our content. The levels of sponsorship listed are reflective of the amount of funding given. View funders.
Now you can support HCPs in making informed decisions for their patients
Your contribution helps us continuously deliver expertly curated content to HCPs worldwide. You will also have the opportunity to make a content suggestion for consideration and receive updates on the impact contributions are making to our content.
Find out more
Create an account to access:
Bookmark & personalize site content
Receive alerts for new content in your areas of interest
View AML content recommended for you
Phase III LACEWING trial: Gilteritinib + azacitidine vs monotherapy in ND FLT3m AML
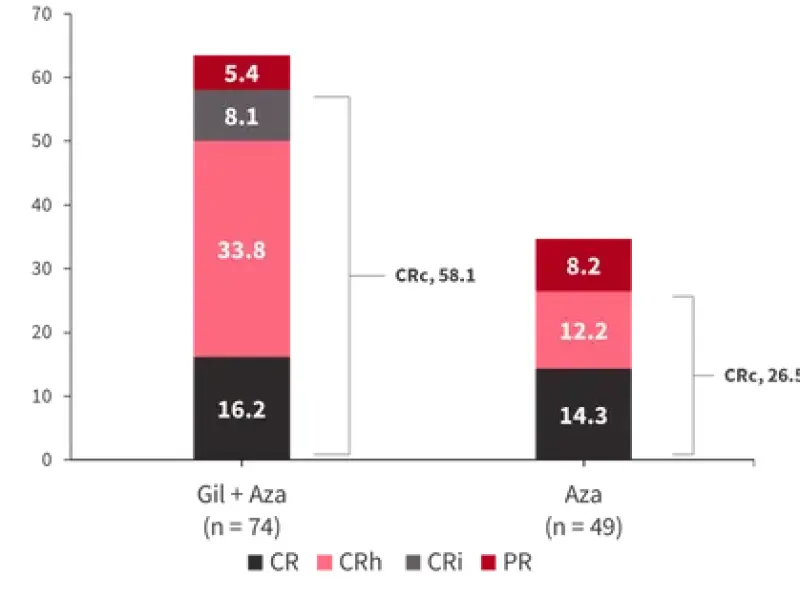
Results from the final analysis of the randomized, open-label, phase III LACEWING study (NCT02752035) evaluating gilteritinib + azacitidine (Aza; n = 104) vs Aza (n = 57) or gilteritinib (n = 22) monotherapy in adults with newly diagnosed (ND) FLT3-mutated (FLT3m) acute myeloid leukemia (AML) ineligible for intensive chemotherapy (IC) were published in Haematologica by Wang et al. The primary endpoint was overall survival (OS).
Key data: At a median follow-up of 30.1 months with gilteritinib + Aza and not estimable (NE) with Aza, median OS was 9.82 months vs 9.23 months, respectively (hazard ratio [HR], 0.829; p = 0.182). Median OS with gilteritinib was 5.24 months, with a NE median follow-up. The overall response rate (ORR) was 70.2% with gilteritinib + Aza vs 36.8% with Aza (p < 0.001) and 72.7% with gilteritinib. In subgroup analysis, median OS was longer with gilteritinib + Aza vs Aza in patients with FLT3-internal tandem duplication (ITD) AML without a tyrosine kinase domain (TKD) mutation (11.63 months vs 8.87 months; nominal p = 0.047) and in those with a high FLT3-ITD allelic ratio (≥0.5; 11.89 months vs 7.46 months; nominal p = 0.016). Treatment-related adverse events (TRAEs) were more frequent with gilteritinib + Aza vs Aza; the most common Grade ≥3 TRAEs were neutropenia (24.3% vs 20.4%), febrile neutropenia (24.3% vs 7.4%), thrombocytopenia (18.4% vs 13.0%), and anemia (18.4% vs 16.7%).
Key learning: In this study, gilteritinib + Aza did not improve median OS vs Aza in patients with ND FLT3m AML ineligible for IC. Nominal OS benefits were observed in patients with FLT3-ITD without a TKD mutation and in those with a high FLT3-ITD allelic ratio, but these findings require further evaluation.
References
Please indicate your level of agreement with the following statements:
The content was clear and easy to understand
The content addressed the learning objectives
The content was relevant to my practice
I will change my clinical practice as a result of this content